
Why I-MED Radiology
At I-MED Radiology, when you need answers, we are here to provide the highest quality care and deliver the most accurate diagnostic outcomes ...

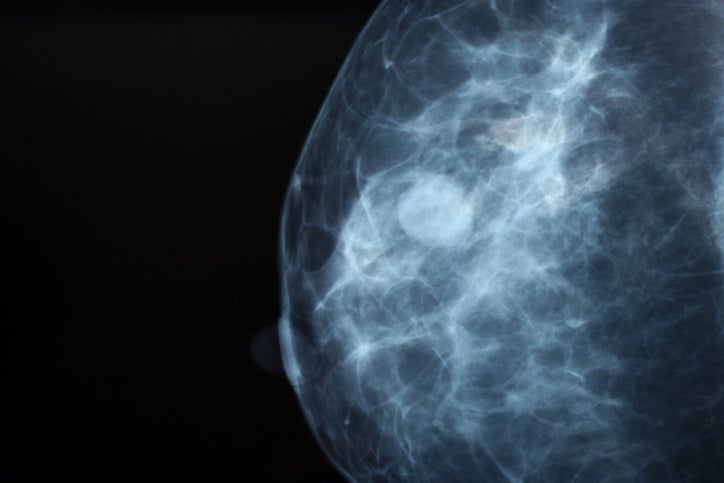
If an abnormality that cannot be easily felt in the breast needs to be surgically removed, surgeons need a marker to guide to the correct area of breast tissue. A hookwire localisation is where a fine wire, called a hookwire, is placed in the breast with its tip at the site of the abnormality.
Before surgery is carried out, a radiologist places the hookwire into the correct position in the breast using ultrasound, mammography or MRI for guidance. The ‘hook’ at the end of the wire prevents the wire from moving out of position before surgery.
Breast hookwire localisation is carried out using local anaesthetic to numb the breast in the area where the hookwire is to be inserted.
If you have an abnormality in your breast that cannot be easily felt, but requires surgical removal, a hookwire can be used as a marker for the surgeon. A hookwire gives the surgeon an accurate location of the lump prior to surgery.
There is no preparation required for the hookwire localisation.
You should bring any previous imaging scans and reports with you so these can be reviewed by our radiologist before your procedure.
The radiologist will choose the method of imaging guidance for the localisation (i.e. mammography, ultrasound or MRI), usually depending on which type of imaging originally found the abnormality, and which type of imaging shows the area most clearly.
Mammographic imaging guidance
A mammogram will be carried out with the breast placed between two plates and compressed, and the radiologist will find the abnormality. The breast remains compressed for the duration of the procedure. The breast is washed with antiseptic and the radiologist will place a very fine needle into the breast with local anaesthetic to numb the area where the hookwire is to be inserted.
The radiologist will then insert a fine needle into the breast tissue that is to be removed. Mammographic images are taken to check the needle is in the correct position and the needle is adjusted as required. Once the needle is in the correct position, a fine wire is passed down the centre of the needle and the needle is removed, leaving the wire in place. A final mammogram is carried out to show the surgeon where the tip of the wire lies in relation to the abnormality that is to be removed.
Ultrasound imaging guidance
The radiologist will find the abnormality using images taken with an ultrasound probe.The breast is washed with antiseptic, and the radiologist will place a very fine needle into the breast with local anaesthetic to numb the area where the hookwire is to be inserted.
The radiologist will then insert a fine needle into the tissue that is to be removed. The position of the needle is checked using the ultrasound images. Once the needle is in the correct position, a fine wire is passed down the centre of the needle and the needle is removed, leaving the wire in place. A final mammogram is carried out to show the surgeon where the tip of the wire lies in relation to the abnormality that is to be removed.
MRI scan guidance
An intravenous line will be inserted, usually into a vein in the arm or back of the hand or wrist. You will then be positioned on a bed that moves in and out of the MRI scanner. The breast will be lightly compressed from the side by a small plastic plate. An injection of dye or contrast medium will usually be given into the intravenous line to highlight and provide a clearer picture of the breast area on the MRI images. A set of MRI scans will be carried out.
The breast is washed with antiseptic, and the radiologist will place a very fine needle into the breast with local anaesthetic to numb the area where the hookwire is to be inserted. The radiologist will then insert a plastic needle into the abnormal tissue. Once the needle is in the correct position, a fine wire is passed down the centre of the needle and the needle is removed, leaving the wire in place. The MRI scanner produces pictures to show the surgeon where the tip of the wire lies in relation to the abnormality that is to be removed.
Whichever method is used for guidance of the hookwire placement, a piece of the fine wire is left sticking out from the breast. After the procedure, this piece of wire is taped down to the skin, and the hookwire remains in the abnormality in the breast. The surgeon will remove the wire together with the abnormality at the time of the operation. Your previous imaging and the images from the breast hookwire localisation will be sent with you to the operating theatre, so that the surgeon can refer to them during the surgery.
As the hookwire will be removed at the time of the operation, there are no after effects of the procedure itself.
Mammographic and ultrasound-guided hookwire localisations take approximately 30 minutes. An MRI-guided procedure requires approximately 45 minutes.
Hookwire localisation is a simple procedure and most women have no problems. Some problems that can occur are:
Hookwire localisation assists a surgeon in the removal of breast abnormalities that cannot be felt. It marks where the abnormal tissue is located and enables the surgeon to remove even the smallest amount of abnormal tissue identified on mammograms, ultrasound or MRI scans. As only the abnormal tissue is removed (with a margin of clear tissue around it), scarring can be minimised and the shape of the breast can be preserved as far as possible. This also reduces the time taken for the operation to be completed, which is important when you are having a general anaesthetic.
Your doctor will receive a written report on your test as soon as is practicable.
It is very important that you discuss the results with the doctor who referred you so they can explain what the results mean for you.
Most results are normal. Occasionally, small changes are seen that need further review.
If your results are normal you will be able to return for routine screening (usually every 2 years). If your results are uncertain or show changes you may need to consider additional imaging (ultrasound, or biopsy) in discussion with your referring doctor.

This information has been reviewed and approved by Dr Ronald Shnier (I-MED Chief Medical Officer).
This information has been reviewed and approved by Dr Ronald Shnier (I-MED Chief Medical Officer).